
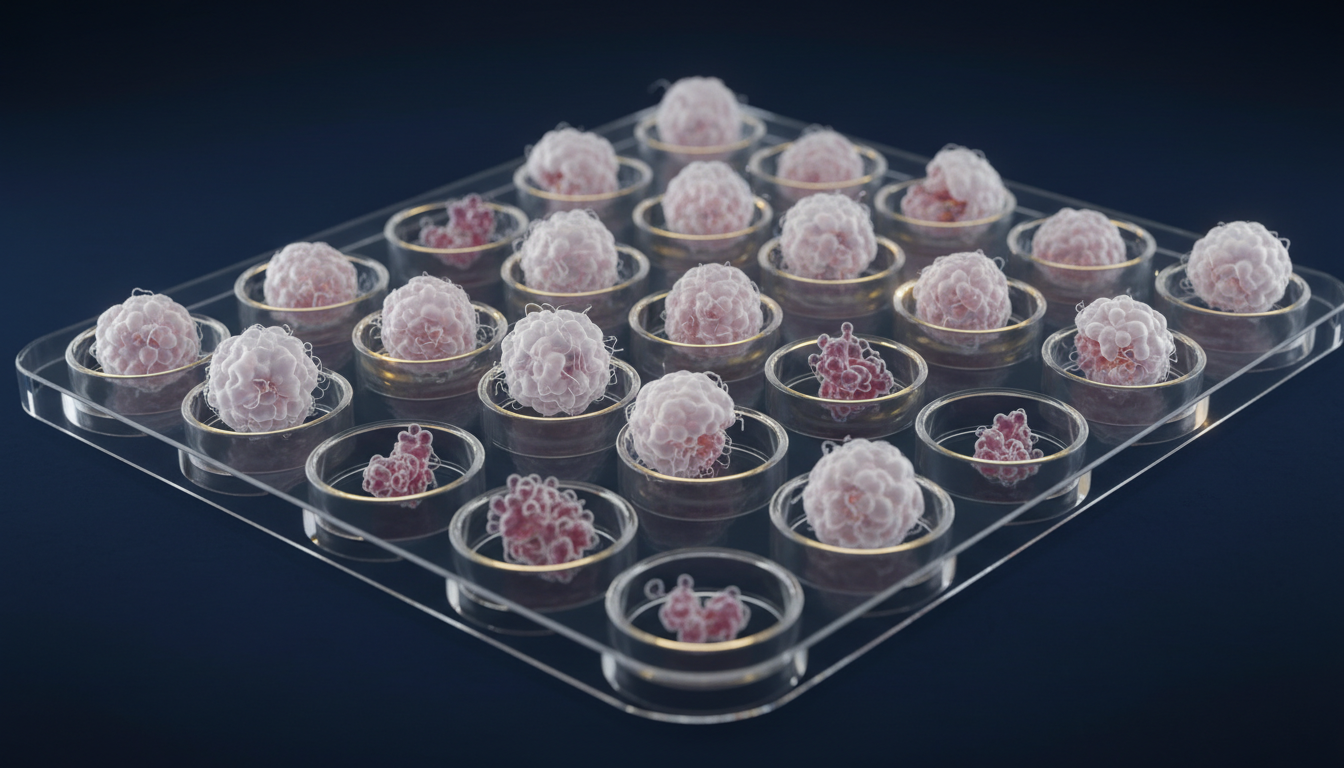
Most cancer treatment decisions are made from statistics: a drug is chosen because it helped a certain percentage of people with the same diagnosis in a clinical trial. Genomic testing narrows that choice by reading the cancer’s DNA. Chemosensitivity testing asks a more direct question. It takes a patient’s own living cancer cells, exposes them to treatments in the laboratory, and measures which ones actually damage or kill them. This article explains how the testing works, what the newest studies show about how well it predicts real-world response, and where it is available.
What Chemosensitivity Testing Is
Chemosensitivity testing, also called functional drug testing or functional precision medicine, is a laboratory test of how a person’s cancer cells respond to treatment. The term covers several methods, but the principle is the same in all of them: rather than predicting response from a list of mutations, the laboratory watches the response happen.
This matters because two cancers with the same mutation can respond very differently to the same drug. A mutation report tells you what the cancer is built from. A functional test tells you what the cancer does when a drug reaches it. The two approaches answer different questions and work best together.
The Main Types of Functional Testing
Organoids: growing the tumor in miniature
Patient-derived organoids are tiny three-dimensional copies of a tumor grown from a biopsy or surgical sample. Because they grow in three dimensions, they keep much of the original tumor’s structure, mix of cell types and genetic makeup. Once grown, each organoid line can be tested against dozens of drugs at once. Organoids are currently the best-studied form of functional testing for solid tumors.
Short-term tissue cultures
Cells from a fresh tumor sample are kept alive for days rather than weeks and exposed to drugs. Results come back faster than with organoids, though the cells drift further from the original tumor the longer they are kept outside the body.
Single-cell imaging screens
For blood cancers such as leukemia and lymphoma, cancer cells can be taken from blood or bone marrow, exposed to drugs, and photographed under automated microscopes. Software then counts how many cancer cells each drug kills compared with normal cells in the same sample.
Blood-based testing of circulating tumor cells
Some laboratories, mainly in Europe, isolate circulating tumor cells from an ordinary blood sample and test them against chemotherapy drugs, targeted drugs, repurposed drugs and natural compounds. The great advantage is that no biopsy is needed and the test can be repeated over time. Published validation studies for this approach are fewer than for organoids, so it is best read alongside sequencing and other tests rather than alone.
What the Evidence Shows
Organoids predicted response in gastrointestinal cancers (United Kingdom)
In a landmark 2018 study from the Institute of Cancer Research in London, organoids grown from patients with metastatic colorectal and gastroesophageal cancers were tested against the same drugs the patients were receiving. The organoids correctly identified every patient whose cancer would not respond (100% sensitivity), and when an organoid responded, the patient responded 88% of the time.1
Organoids identified who would not benefit from irinotecan (the Netherlands)
Researchers at the Netherlands Cancer Institute grew organoids from metastases of colorectal cancer. For irinotecan-based chemotherapy, the organoid test predicted the response of the biopsied tumor in more than 80% of patients without wrongly excluding anyone who would have benefited.2 This points to one of the most valuable uses of functional testing: sparing patients months of a treatment that will not work for their cancer.
The 2025 colorectal study: linked to survival
A study published in Clinical Cancer Research in December 2025 tested organoids from metastatic colorectal cancer against standard treatments. For 5-fluorouracil and oxaliplatin, the organoid result was correct about 80% of the time whether it predicted response or non-response, and patients whose organoids were sensitive lived longer without progression and lived longer overall than patients whose organoids were resistant. Just as useful, organoids that resisted the standard drugs often showed sensitivity to other treatments, pointing to alternatives.3
Ovarian cancer and PARP inhibitors (2025)
A 2025 study of advanced ovarian cancer found that organoid testing predicted response to first-line carboplatin and paclitaxel with about 92% accuracy in the patients who could be evaluated. It also caught cases that genetic testing alone would have gotten wrong: one tumor with the genetic marker that usually predicts response to PARP inhibitors was resistant in the organoid and in the patient, while two tumors without the marker responded in both.4 This is exactly why functional testing and genomic testing belong together.
The first trial to treat patients by the test result (Austria)
The strongest evidence comes from the EXALT trial at the Medical University of Vienna. Patients with aggressive blood cancers who had run out of standard options had their cancer cells screened against a large drug panel, and their next treatment was chosen from the results. Fifty-four percent of the patients treated this way stayed free of progression at least 30% longer than they had on their previous treatment, and among them the typical gain was more than threefold. Some were exceptional responders with long remissions.5 This was the first prospective trial in oncology to choose individual treatments based on a functional test.
Can It Test Natural Compounds and Repurposed Drugs?
Yes. The laboratory method does not care whether a compound is a patented chemotherapy drug, an older off-patent medicine or a plant extract. Some laboratories include repurposed drugs such as mebendazole, ivermectin and metformin, and natural compounds such as curcumin and artesunate, alongside standard drugs in their panels. Because off-patent medicines and natural compounds cannot be patented, no company will pay for large clinical trials of them. For a patient, a functional test may be the only direct evidence available about whether one of these agents affects their particular cancer.
You can read more about two of the most-asked-about repurposed drugs in our articles on fenbendazole and cancer and ivermectin and cancer.
What the Testing Cannot Yet Do
Knowing the limits makes the results more useful. Most functional tests measure the cancer cells alone, without the patient’s immune system, blood supply or liver metabolism, so they are strongest for drugs that act directly on cancer cells. Predicting response to immunotherapy requires adding the patient’s own immune cells to the test; a 2026 review of these newer tumor-immune organoids found the approach promising but not yet mature.6 Organoids also take time to grow, typically several weeks, and do not grow successfully from every sample. Fresh tissue is usually required, which means planning before a biopsy or surgery rather than after.
Where Chemosensitivity Testing Is Available
Functional testing is not yet part of standard U.S. cancer guidelines, and in the United States it is used mostly in research settings. In Germany, Greece and other European countries, and in parts of Asia, laboratories offer functional testing directly to patients, including blood-based testing that needs no biopsy. Our book, The New Reality of Cancer, describes the main testing methods country by country, how to plan tissue collection so a sample can be tested, and how to read a functional report alongside a genomic one.
Frequently Asked Questions
What is chemosensitivity testing?
It is a laboratory test that exposes a patient’s own living cancer cells to treatments and measures which ones damage or kill them.
How is it different from genomic testing?
Genomic testing reads the cancer’s DNA and predicts response from known mutations. Chemosensitivity testing measures the actual response of living cells. The two complement each other.
How accurate is organoid drug testing?
In published studies of gastrointestinal and ovarian cancers, organoid results matched patient responses roughly 80% to 90% of the time, and they are especially good at identifying treatments that will not work.
Do I need a biopsy?
Organoids and tissue cultures need fresh tumor tissue. Blood-based testing of circulating tumor cells uses an ordinary blood sample.

About the author. Dr. Silver, MD, graduated from Temple University School of Medicine, trained as an interventional cardiologist, and has practiced medicine for nearly fifty years. A lymphoma survivor of about twenty-five years, he is co-author, with Dr. Lindmeier, DHSc, of The New Reality of Cancer: The Science of Recovery. Read more about Dr. Silver, MD.
Research by Dr. Lindmeier, DHSc, cancer educator and co-author of The New Reality of Cancer.
More articles on advanced cancer testing and all articles.
References
- Vlachogiannis G, Hedayat S, Vatsiou A, et al. Patient-derived organoids model treatment response of metastatic gastrointestinal cancers. Science. 2018;359(6378):920–926.
- Ooft SN, Weeber F, Dijkstra KK, et al. Patient-derived organoids can predict response to chemotherapy in metastatic colorectal cancer patients. Science Translational Medicine. 2019;11(513):eaay2574.
- Patient-derived organoids predict treatment response in metastatic colorectal cancer. Clinical Cancer Research. 1 December 2025. doi:10.1158/1078-0432.CCR-25-1564
- Patient-derived organoids predict responses to chemotherapy and PARP inhibitors in advanced ovarian cancer. Journal of Translational Medicine. 2025. doi:10.1186/s12967-025-07112-y
- Kornauth C, Pemovska T, Vladimer GI, et al. Functional precision medicine provides clinical benefit in advanced aggressive hematologic cancers and identifies exceptional responders. Cancer Discovery. 2022;12(2):372–387.
- Patient-derived tumour-immune organoids as functional biomarkers of checkpoint-inhibitor response: a systematic review and exploratory meta-analysis. medRxiv preprint. August 2026.
This article is for education only. It is not medical advice and does not diagnose or treat any condition. Cancer Expert MD has no financial relationship with any laboratory, drug maker, supplement company, clinic or hospital.
Responses
[…] testing can answer this more directly. Chemosensitivity testing, offered by laboratories in Europe and elsewhere, exposes a patient’s own living cancer cells […]
[…] Chemosensitivity testing can include mebendazole and show directly whether a patient’s own cancer cells respond to it. For how mebendazole compares with its veterinary relative, see our article on fenbendazole and cancer. Our book, The New Reality of Cancer, organizes repurposed drugs by the cancer pathways they act on. […]
[…] Metformin is often combined with a low-glycemic or ketogenic diet, which also lowers insulin. Chemosensitivity testing can also include metformin to show whether a patient’s own cancer cells respond to […]
[…] markers of cancer stem cells. We explain this and the organoid-based approaches in our article on chemosensitivity testing. Published validation for blood-based drug testing is thinner than for counting, so the results are […]
[…] articles on advanced cancer testing, including chemosensitivity testing, and all […]